
The Emergency Department as the Gateway: When Infection is Not the Answer in the Older Adult
DOI:
https://doi.org/10.24950/rspmi.2809Keywords:
Aged, Anti-Neutrophil Cytoplasmic Antibody-Associated Vasculitis Fever of Unknown OriginAbstract
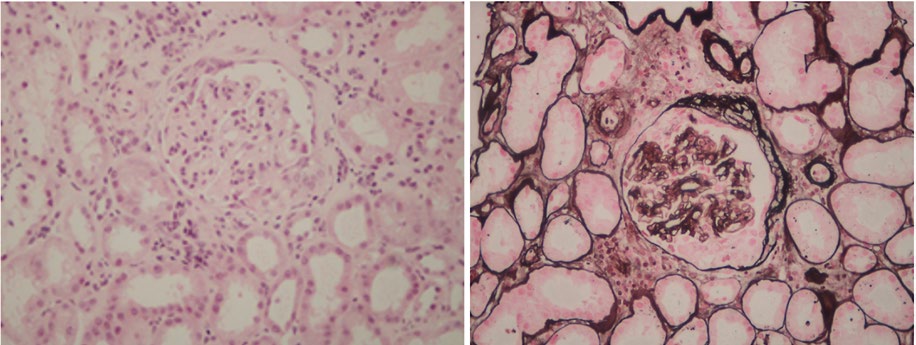
Symptoms suggestive of infection, such as fever, cough, or dysuria, are frequent reasons for presentation to the Emergency Department (ED), and infection is often assumed during the initial assessment of older adults. However, not all suspected infections are ultimately confirmed. We describe a 70-year-old male adult with a one-month history of headache, myalgias and fatigue. Dry cough, tachypnoea, and low-grade fever (38.1ºC) were noted in the emergency room. Despite initial suspicion of infection, the infectious workup was negative. Anti–myeloperoxidase antineutrophil cytoplasmic antibodies serology (MPO-ANCA) and renal biopsy established the diagnosis of small-vessel vasculitis with crescentic pauci-immune glomerulonephritis, treated with corticosteroids and rituximab. This case highlights that not all acute presentations resembling infection in older adults have infectious origins and underscores the importance of maintaining a broad differential diagnosis to ensure timely and appropriate management.
Downloads
References
1. Hofman MR, van den Hanenberg F, Sierevelt IN, Tulner CR. Elderly patients with an atypical presentation of illness in the emergency department. Neth J Med. 2017;75:241-6.
2. Tal S, Guller V, Gurevich A. Fever of unknown origin in older adults. Clin Geriatr Med. 2007;23(3):649-668, viii. doi:10.1016/j.cger.2007.03.004.
3. Natour HH, Elgardt I, Rotman-Pikielny P, Natour A, Natour A, Levy Y. Masquerading Pulmonary Embolism: Fever as an Overlooked Clinical Manifestation Illustrated by Four Mini Case Series and Literature Review. Am J Med. 2025;138:1124-7. doi:10.1016/j.amjmed.2025.02.026
4. Wilke L, Prince-Fiocco M, Fiocco GP. Microscopic polyangiitis: a large single-center series. J Clin Rheumatol. 2014;20:179-82. doi:10.1097/RHU.0000000000000108
5. Jennette JC, Falk RJ, Bacon PA, Basu N, Cid MC, Ferrario F, et al. 2012 revised International Chapel Hill Consensus Conference Nomenclature of Vasculitides. Arthritis Rheum. 2013;65:1-11.
6. Hashmi MF, Rout P. Microscopic Polyangiitis. 2024 In: StatPearls [Internet]. Treasure Island: StatPearls Publishing; 2026
7. Giua R, Pedone C, Onetti Muda A, Antonelli Incalzi R. Fever of unknown origin in a very old patient: beware of the kidney! Aging Clin Exp Res. 2014;26:539-42. doi:10.1007/s40520-014-0200-8
8. Harper L, Savage CO. ANCA-associated renal vasculitis at the end of the twentieth century--a disease of older patients. Rheumatology. 2005;44:495-501. doi: 10.1093/rheumatology/keh522.
9. Petersdorf RG, Beeson PB. Fever of unexplained origin: report on 100 cases. Medicine. 1961;40:1.
10. Teng JH, Wu PH, Chuang CH, Liang PI, Chen GX. A Critical Case of MPO-ANCA-Associated Vasculitis with an Initial Presentation of Fever of Unknown Origin. Research Square. Preprint posted online May 23, 2024. doi:10.21203/rs.3.rs-4277207/v1
11. Fernandez C, Beeching NJ. Pyrexia of unknown origin. Clin Med. 2018;18:170-4. doi:10.7861/clinmedicine.18-2-170
12. Shields O, Shah A, Mann B. Pyrexia of unknown origin and pulmonary fibrosis as a presentation of MPO-ANCA associated vasculitis. BMJ Case Rep. 2011;2011:bcr0120113692. doi:10.1136/bcr.01.2011.3692
13. Norman DC. Fever in the Elderly. Clin Infect Dis. 2000;31:148-51. doi:10.1086/313896
Downloads
Published
How to Cite
Issue
Section
Categories
License
Copyright (c) 2026 Portuguese Journal Internal Medicine

This work is licensed under a Creative Commons Attribution 4.0 International License.








